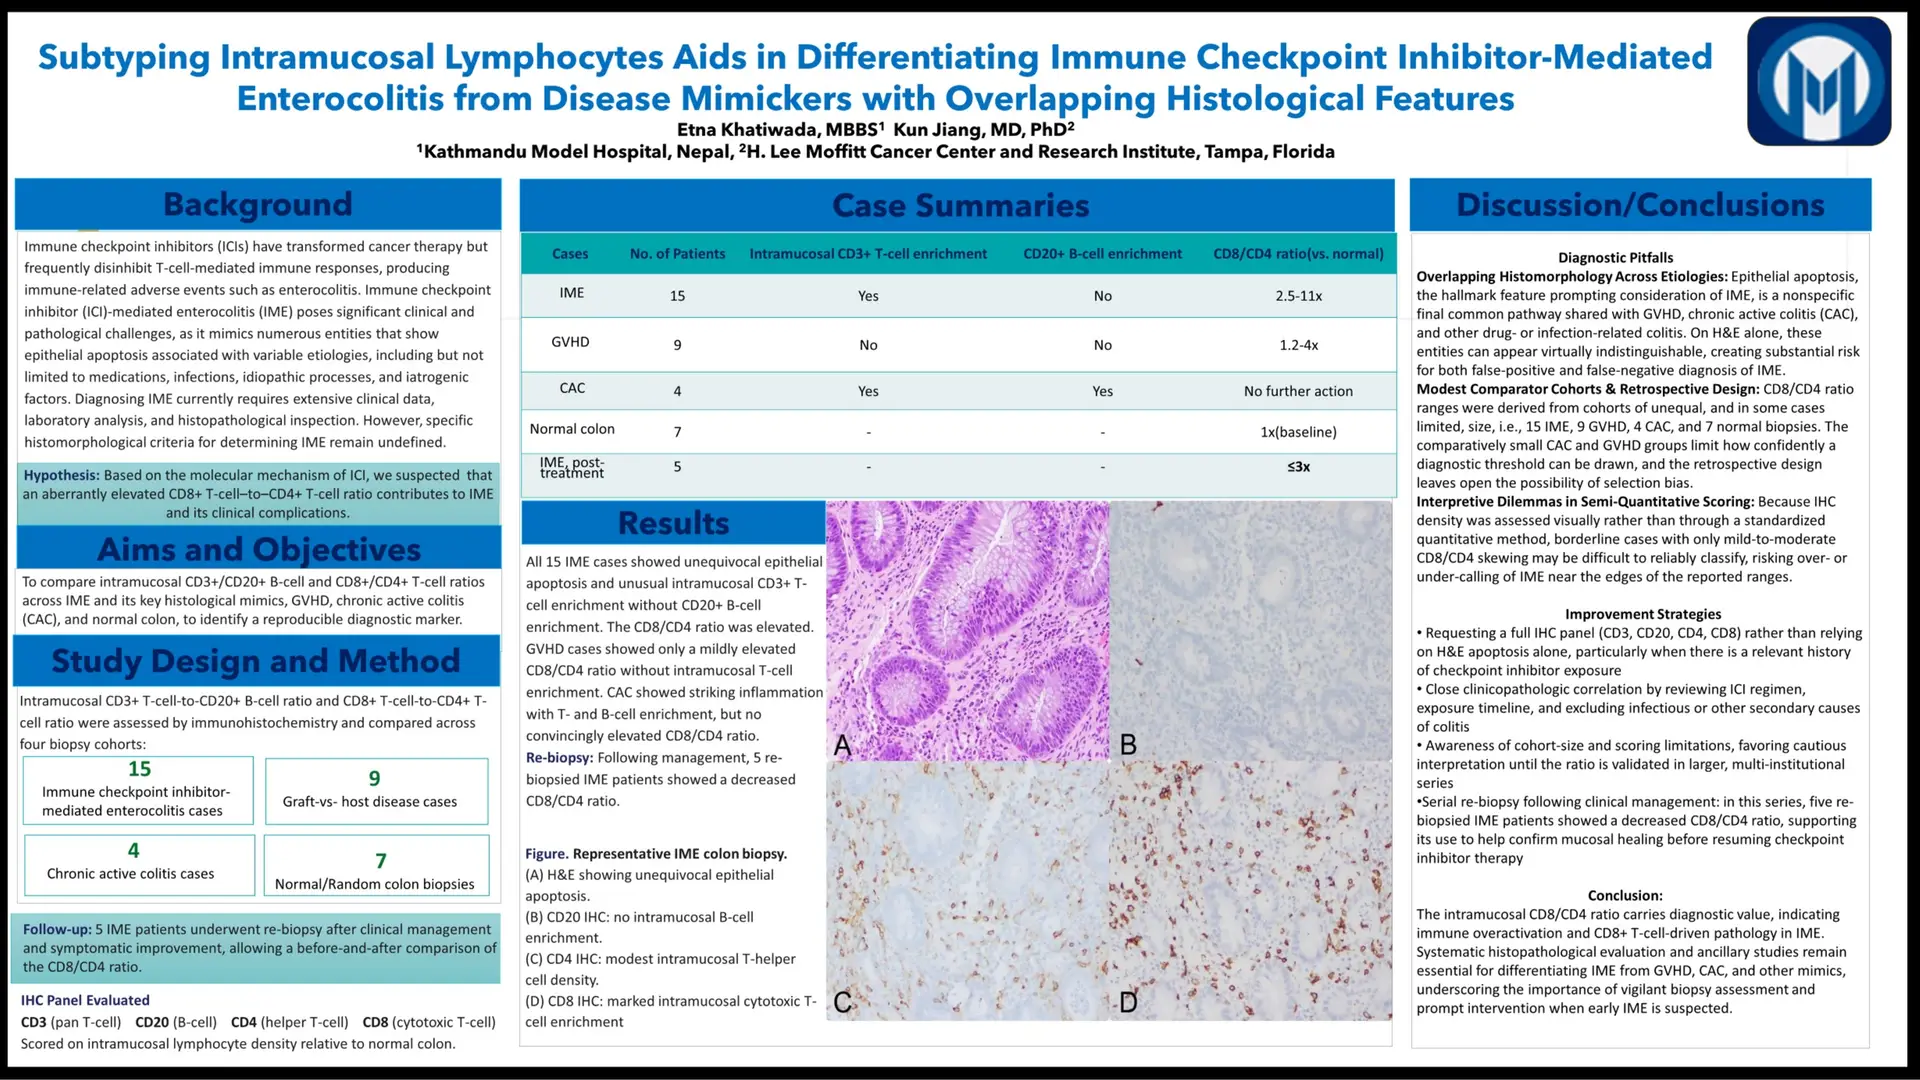
Immune checkpoint inhibitor (ICI)-mediated enterocolitis (IME) poses clinical and pathological challenges, as it mimics many entities that show epithelial apoptosis associated with variable etiologies, including, but not limited to, medications, infections, idiopathic processes, and/or iatrogenic factors. Diagnosing IME requires extensive clinical data, laboratory analysis, and histopathological inspection. However, specific histomorphological criteria for determining IME remain undefined.
Based on the molecular mechanism of ICI, we suspect that an aberrantly elevated CD8+T-cell–to–CD4+T-cell ratio contributes to IME and its clinical complications. The intramucosal CD3+T-cell-to-CD20+B-cell ratio and CD8+T-cell-to-CD4+T-cell ratio were reviewed and compared among 15 IME, 9 graft-versus-host disease (GVHD), 4 chronic active colitis (CAC), and 7 random normal colon biopsies.
All 15 IME cases showed unequivocal epithelial apoptosis (Figure A) and unusual intramucosal CD3+T-cells enrichment without CD20+B-cells enrichment (Figure B). There was an elevated CD8 (Figure D)/CD4 (Figure C) ratio, i.e., 2.5- to 11-fold of the normal colon. Similarly, GVHD cases showed a mildly elevated CD8/CD4 ratio (1.2 to 4-fold of normal) but without intramucosal T-cell enrichment. Despite striking inflammation and enrichment of T- and B-cells in CAC, no convincingly elevated CD8/CD4 ratio was identified. Interestingly, following management and symptomatic improvement, 5 re-biopsies of IME patients showed a decreased CD8/CD4 ratio within 3-fold of normal.
This study illustrated the potential diagnostic value of the intramucosal CD8/CD4 ratio, indicative of immunity-overactivation and CD8+T-cell-related IME. Nevertheless, systematic histopathological evaluation and ancillary studies remain crucial for differentiating IME from GVHD, CAC, and other mimics. These findings underscore the importance of vigilant biopsies and prompt intervention while facing potentially early IME.